BERGEM·HEALTH
Home › Treatments › Pain Management
Pain Management
SPECIALITY · PAIN MANAGEMENT

Pain management in Türkiye — chronic pain, neuromodulation, interventional blocks.

Radiofrequency ablation, spinal cord stimulation, multimodal pain approach.

What you get
  • Pain specialist + physiotherapist + psychologist on team
  • 24/7 interventional pain
  • Spinal cord stimulation (SCS)
2 centres · 4 pain specialists · multimodal team
SECOND OPINION ONLINE

Video consultation with a pain specialist — free

Describe pain character (VAS, duration), send your MRI — the pain specialist designs a multimodal plan.

01
Upload your discharge summary
Discharge summaries, CT/MRI discs (DICOM), histology slides if available. Up to 200 MB.
02
Coordinator reviews
Selects 2–3 professors matched to your diagnosis and stage. Sends them your records.
03
Video consultation
The professor responds online — review of histology, protocol, travel plan if needed.
What to send
  • Discharge summaries from inpatient / outpatient care
  • CT or MRI — original DICOM discs
  • Histology report (if available)
  • Slides or blocks for review (optional)
  • Current therapy list
Request a second opinion
Free. Confidential. Anna Moroz reads every request personally.
5 PROCEDURES

Pain conditions we treat

Chronic back pain, neuropathic pain, headache, cancer pain.

TREATMENT METHODS

Pain management methods

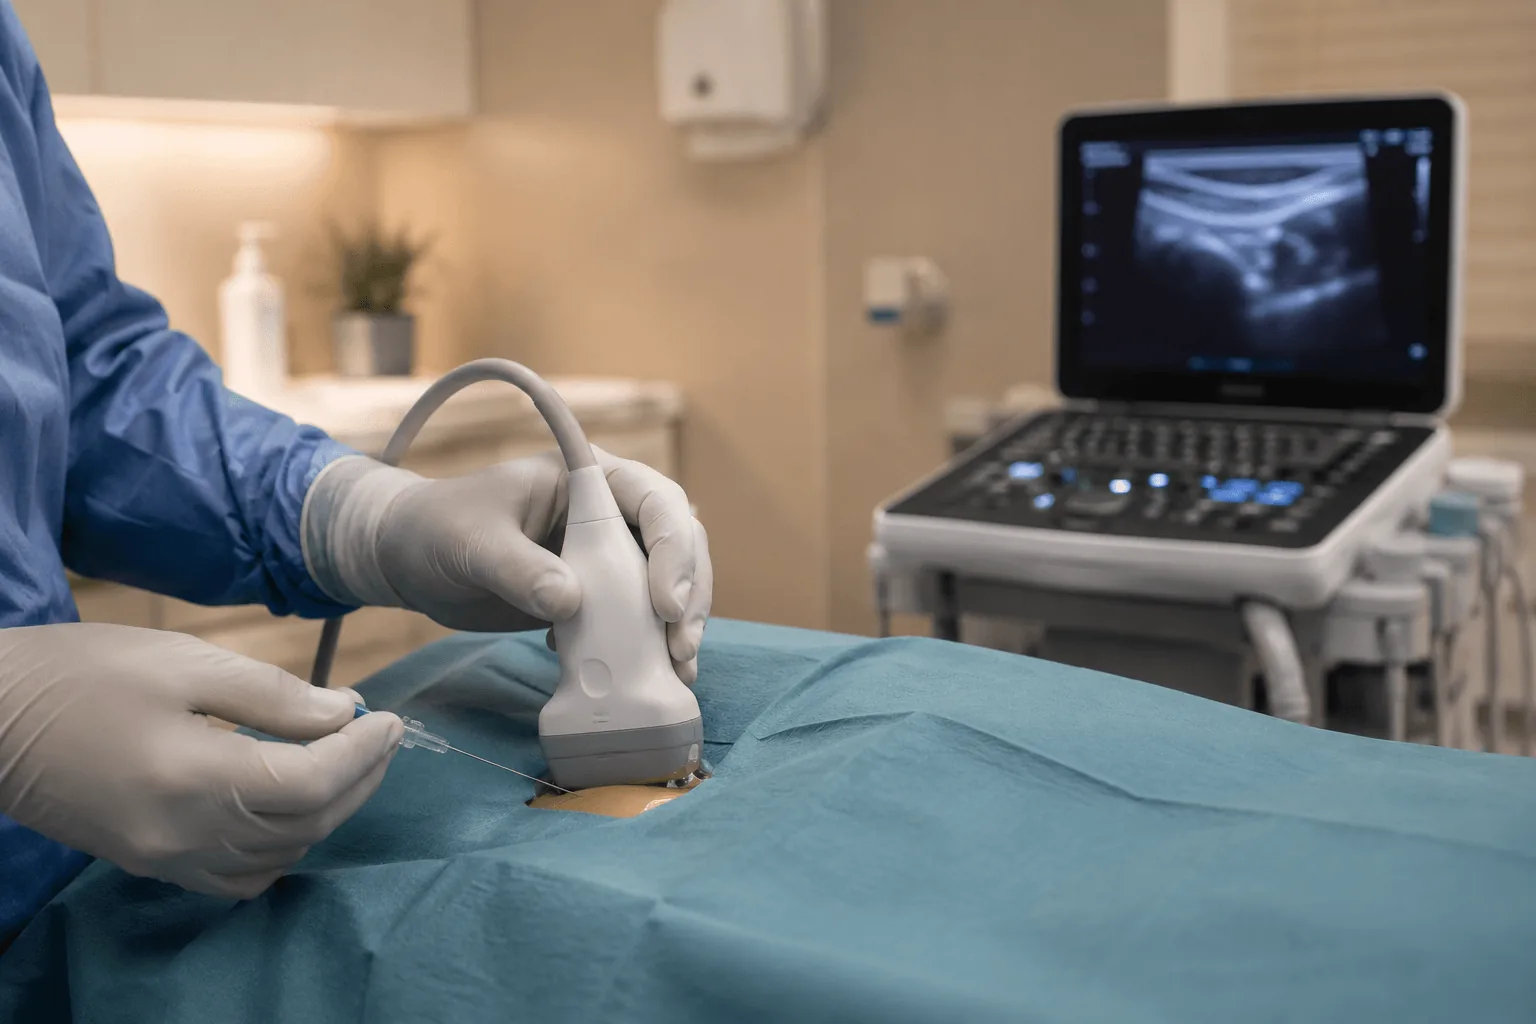
Interventional blocks, RFA, neuromodulation, botulinum therapy, multimodal pharmacotherapy.

Radiofrequency ablation (RFA)
Targeted coagulation of facet joint nerves.
2 clinics
Epidural steroid blocks
Fluoroscopy-guided for radiculopathy.
2 clinics
SCS (spinal cord stimulation)
For chronic neuropathic pain and FBSS.
1 clinic
Botulinum therapy
For chronic migraine and dystonia.
2 clinics
PAIN MANAGEMENT · TEAM

Professors you get direct access to

Professors and senior specialists at Memorial, Liv and Akdeniz. Direct contact, no middlemen.

DIAGNOSTICS

Pain diagnostics

MRI, ENMG, diagnostic blocks, nerve biopsy, DN4/PainDETECT questionnaires.

Spine MRI 3T
Assessment of discs, facet joints and nerve roots.
1 day
ENMG
Differentiating muscular vs neurological pain causes.
1 hour
Diagnostic blocks
Confirming pain source before RFA.
1 day
Pain questionnaires
VAS, DN4, PainDETECT — standardised assessment.
15 min
PRICE SNAPSHOT

Pain management pricing — Türkiye vs EU/USA

Minimum prices, for reference only. The final cost is calculated individually after the doctors review your records.

Procedure Türkiye EU / USA Savings
Epidural block from $400 $1 500 – 3 000 −72%
RFA of facet joints from $1 500 $5 000 – 9 000 −72%
SCS (system implantation) from $15 000 $50 000 – 90 000 −75%
Botox for migraine (1 session) from $500 $1 800 – 3 200 −72%
The information on this page is for reference only and does not constitute a medical opinion.
Request a precise quote for my case
QUESTIONS

Frequently asked about Pain Management

My chronic back pain hasn't responded to physiotherapy - is interventional pain management next?
After 6-12 weeks of structured physiotherapy, NSAIDs and lifestyle measures fail, interventional options enter the algorithm. We re-image with MRI, identify the pain generator (disc, facet, sacroiliac, nerve root) and offer ultrasound- or fluoroscopy-guided injections, radiofrequency ablation, or epidural therapy. Surgery is reserved for clear neurological deficit or instability.
How effective is radiofrequency ablation for sacroiliac joint pain?
After a positive diagnostic SI joint block (>50-80% pain relief), lateral branch radiofrequency ablation provides 6-12 months of significant relief in 60-70% of patients, often longer with repeat treatment. The 30-45 minute outpatient procedure under ultrasound or fluoroscopy denatures the sensory nerves supplying the joint. Memorial and Liv pain clinics charge roughly $1,500-2,500 versus $5,000-10,000 in EU centers.
Does an epidural steroid injection really work for sciatica?
For acute lumbar radicular pain from a herniated disc, transforaminal epidural steroid injection under fluoroscopy can give short-term relief in some patients; evidence that it prevents surgery in the long term is limited. Effect is smaller for chronic radiculopathy or spinal stenosis. We typically allow up to 3 injections per year. Serious complications are rare; a temporary rise in blood sugar is common in people with diabetes, and rare serious neurological events have been reported with transforaminal injections.
Am I a candidate for a spinal cord stimulator?
Spinal cord stimulation is considered for failed back surgery syndrome, CRPS, painful diabetic neuropathy or refractory radiculopathy after at least 6 months of conservative care. A psychological evaluation, MRI and a 5-7 day percutaneous trial come first; if pain drops >=50% during the trial, a permanent device is implanted. Long-term success - sustained >=50% relief - is reported in 55-70% of selected patients.
Can an intrathecal pump help my cancer pain?
Yes - for patients on high-dose oral or transdermal opioids with inadequate relief or intolerable side effects, an intrathecal morphine or morphine-bupivacaine pump delivers 1/300 of the oral dose directly to the CSF. It typically cuts pain scores by 50-70% and reduces sedation, nausea and constipation. Implant takes 60-90 minutes; programming and refills are done in clinic every 1-3 months.
How do you treat fibromyalgia - I've already tried multiple medications?
Fibromyalgia needs a multimodal protocol, not single-drug fixes. Our pain team combines duloxetine or pregabalin, graded aerobic exercise, CBT, sleep optimization, and trigger-point therapy. Off-label options such as low-dose naltrexone, IV lidocaine or ketamine have not shown convincing benefit in fibromyalgia and are not part of routine care. We also screen for and treat coexisting depression, sleep apnea and small-fiber neuropathy that frequently mimic refractoriness.
I want to come off long-term opioids - how is that managed safely?
We design an individualized opioid taper of 5-10% reduction every 1-4 weeks, slower at lower doses. Adjuvants (gabapentinoids, SNRIs, NSAIDs, topical agents), interventional procedures and CBT replace lost analgesia. Buprenorphine rotation is offered for high-dose or complex patients. Withdrawal symptoms are managed with clonidine, antiemetics and hydration. Full wean typically takes 3-9 months and is supervised weekly.
REQUEST

Tell me about your case — I’ll read it personally.

Fill in the short form on the consultation page — diagnosis, preferred timing, attached records. We assemble a tumour board for your case and reply within 4 hours.

Open the consultation form
  • Reply within 4 hours during business hours
  • Confidentiality guaranteed
  • Coordinator-translator inside the doctor’s office
  • Tumour board of 2–3 professors within 72 hours
